✦
THE LIFESTYLEMINE NEWSLETTER
Simple wellness tips, healthy recipes, and
everyday inspiration delivered to your inbox.
Your Email Address
Acute gout treatment options:
Colchicine: first-line for acute attacks, and most effective taken within 24 hours of onset. The low-dose protocol (1.2 mg, then 0.6 mg an hour later) works as well as high-dose with far fewer GI side effects.NSAIDs: indomethacin and naproxen for acute attacks; avoid in patients with CKD or peptic ulcer disease.Corticosteroids: prednisone or a corticosteroid joint injection for patients who can’t tolerate colchicine or NSAIDs. Effective, but not for frequent use.
A 2011 New England Journal of Medicine review of gout by Neogi notes that joint aspiration with synovial fluid analysis, identifying MSU crystals under polarized microscopy, is the definitive diagnostic test. Serum uric acid can read normal during an acute attack, which makes the clinical picture more important than the blood test.
Urate-lowering therapy (preventing future attacks): Once someone has had two or more attacks, recurrent tophi, or gout-related joint damage, urate-lowering therapy is indicated. Two agents dominate:
Allopurinol: a xanthine oxidase inhibitor that reduces uric acid production; the most widely used option; target serum urate below 6 mg/dL; titrated up gradually to avoid triggering attacks.Febuxostat (Uloric): a newer xanthine oxidase inhibitor for patients who can’t tolerate allopurinol; FDA approved in 2009.
Diet and gout: Cutting purine-rich foods can lower serum uric acid by about 1 mg/dL, modest but clinically meaningful. The highest-risk foods are organ meats (liver, kidney), anchovies, sardines, mussels, beer (the heaviest purine load among alcoholic drinks), and fructose-sweetened beverages (corn syrup raises uric acid through a separate pathway). Tart cherry extract has been studied for gout prevention; two RCTs by Zhang et al. (2012) and Bell et al. (2014) showed significant drops in attack frequency with daily cherry extract, which is why it appears in the products section below.If you have gout, the broader context of uric acid and kidney function is worth understanding. We cover the kidney’s role in uric acid clearance in our article on chronic kidney disease .
Hallux rigidus: the most common foot arthritis you’ve never heard of
Quick Answer. Hallux rigidus, a cause of big toe joint pain, is osteoarthritis of the first MTP joint. The cartilage between the metatarsal head and the base of the proximal phalanx wears down, causing bone-on-bone grinding, bone spurs, and progressive stiffness. Pain usually worsens during push-off when walking. It’s staged 1 to 4 on the Coughlin-Shurnas classification: Grade 1-2 responds to conservative care, while Grade 3-4 usually needs surgery.
Hallux rigidus, another source of big toe joint pain, is the most common arthritic condition of the foot, and the second most common problem affecting the big toe after bunions. The name is Latin for “stiff big toe,” and stiffness, especially in the upward (dorsiflexion) direction, is the defining symptom of this big toe joint pain. Walking needs roughly 65 degrees of MTP dorsiflexion at push-off, and hallux rigidus progressively limits that range.Coughlin-Shurnas grading scale:
Grade
Findings
ROM loss
Treatment
Grade 1
Mild osteophytes, mild stiffness, normal cartilage
<10%
Stiff-soled shoes, physical therapy, anti-inflammatories
Grade 2
Moderate osteophytes, joint space narrowing, 25–50% ROM loss
Moderate
Carbon fiber insoles, corticosteroid injections, cheilectomy considered
Grade 3
Severe osteophytes, <25% ROM remaining, pain at rest
Severe
Cheilectomy or arthrodesis
Grade 4
Loss of cartilage, bone-on-bone, ankylosis
Near-complete
Arthrodesis (fusion) or MTP joint replacement
According to Coughlin and Shurnas (2003, Journal of Bone and Joint Surgery ) , the largest long-term outcome study of hallux rigidus, cheilectomy (bone spur removal) carries 92% satisfaction at an average 9.9 years of follow-up for Grade 1-2 disease. For Grade 3-4, first MTP arthrodesis (fusing the joint) eliminates pain in 85 to 90% of patients with predictable walking outcomes.Conservative management for Grade 1-2:
Carbon fiber Morton’s extension insoles: the most evidence-supported conservative device for hallux rigidus. They stiffen the shoe through the MTP joint, cutting the dorsiflexion demand on the arthritic joint at push-off, with immediate pain reduction in most patients.Rocker-bottom sole shoes: the curved sole rolls the foot through push-off without requiring MTP extension. Brooks Addiction, New Balance 928, and many stability running shoes build in this feature.Corticosteroid injections: 3 to 6 months of significant relief per injection. They don’t address the underlying degeneration but are valuable for acute flares or pre-surgical management.NSAIDs: ibuprofen or naproxen for flares, not for long-term daily use given the GI and renal risks.
Hallux rigidus surgery options: Cheilectomy: the surgeon removes the bone spurs (osteophytes) from the dorsal aspect of the metatarsal head and proximal phalanx. This doesn’t repair cartilage, but it restores dorsiflexion range and removes the impingement that causes pain with each step. Recovery runs 4 to 6 weeks non-weight-bearing, then a gradual return to activity. Best for Grade 1-2.First MTP arthrodesis (fusion): the arthritic cartilage is removed and the metatarsal head and proximal phalanx are fused with a plate and screws. The joint is permanently immobilized, but pain is eliminated. Patients walk normally on flat surfaces, though high heels and squatting are limited. Recovery is 6 to 8 weeks non-weight-bearing. Best for Grade 3-4 and active people with severe disease.MTP joint replacement: less common, available for specific cases, with longer-term data more limited than arthrodesis.For joint pain management from an anti-inflammatory nutrition angle, the evidence behind turmeric and omega-3s is covered in our turmeric and ginger guide and our anti-inflammatory foods article .
Quick Answer. A bunion, a cause of big toe joint pain, is a deviation of the first ray: the first metatarsal drifts medially (inward) and the big toe drifts laterally (toward the second toe), creating the bony bump on the inner side of the foot. Bunions affect 23 to 35% of adults and are progressive in most cases. Narrow shoes speed up progression but don’t cause bunions; genetics and foot structure are the primary drivers.
Bunion pain, a form of big toe joint pain, comes from two sources: the prominent medial eminence of the first metatarsal head rubbing against shoes (bursitis), and the altered joint mechanics from the angular deformity (arthritis, tendon imbalance). A bunion that’s visible but not painful needs no treatment, and not every bunion produces big toe joint pain. A bunion causing persistent pain, trouble walking, or shoe-fitting problems deserves evaluation.Bunions affect 23 to 35% of adults according to a 2010 systematic review and meta-analysis by Nix et al. (Journal of Foot and Ankle Research ) . Prevalence rises with age and is significantly higher in women, partly explained by footwear history and partly by intrinsic biomechanical differences.
Conservative management:
Wide toe-box shoes: the single most impactful change for reducing daily pain. Shoes should fit the full width of the forefoot without pressing on the medial eminence.Toe spacers: silicone or foam spacers between the first and second toe reduce angular pressure and slow progression, and work best in earlier-stage bunions. Podiatrist-designed spacers (like Correct Toes) position more precisely than generic drugstore options.Bunion splints (night splints): worn during sleep to hold corrected alignment. They don’t reverse the deformity in adults (bones don’t remodel in adults the way they do in children), but they ease symptoms and may slow progression.Wider footwear with metatarsal pads: reduces pressure on the ball of the foot and redistributes metatarsal head loading.
Bunion surgery (bunionectomy): Surgery comes into play when bunion pain is severe, disabling, or unresponsive to at least 3 to 6 months of conservative care. The procedure depends on the severity of the deformity. Mild bunions: a simple osteotomy (metatarsal head shaving). Moderate bunions: a distal chevron or scarf osteotomy (cutting and repositioning the metatarsal to correct alignment). Severe bunions: the Lapidus procedure (first tarsometatarsal joint fusion to correct the root instability). Recovery ranges from 4 weeks to 3 months depending on the procedure. Bunion surgery isn’t cosmetic; it’s functional correction, and recurrence is possible if footwear habits don’t change afterward.
Quick Answer. Turf toe, a cause of big toe joint pain, is a sprain of the plantar capsuloligamentous complex of the first MTP joint, the soft-tissue structures on the underside of the joint that stop excessive dorsiflexion. It typically happens when the forefoot is planted and the heel rises fast while the toe is forced upward, as in sprinting off artificial turf. Mild cases clear in 1 to 2 weeks; severe cases (a complete ligament tear) can sideline athletes for 3 to 6 months.
Turf toe, a cause of big toe joint pain, disproportionately affects athletes in cleated sports on artificial turf, American football, soccer, and rugby, because flexible cleated shoes plus the hardness of artificial turf allow more MTP hyperextension than traditional shoes on natural grass. The name comes from the surface, not the activity, though the result is the same big toe joint pain.Grading:
Grade 1: stretched plantar plate, no instability, tenderness. Treatment: rest, ice, taping, and the RICE protocol for 3 to 5 days.
Grade 2: partial tear, moderate swelling and bruising. Treatment: 2 to 3 weeks in a rigid boot with toe-spica taping; no return to sport until pain-free.
Grade 3: complete tear or sesamoid fracture, significant instability. Treatment: 4 to 8 weeks non-weight-bearing; surgery considered if sesamoid diastasis or chronic instability develops.
Rigid insoles that limit MTP dorsiflexion are the key rehab device for returning to sport. The same carbon fiber insoles used for hallux rigidus give excellent turf toe protection during recovery.
Sesamoiditis: the underdiagnosed source of forefoot pain
Quick Answer. Sesamoiditis, a forefoot cause of big toe joint pain, is inflammation of the two pea-sized sesamoid bones embedded in the flexor hallucis brevis tendon beneath the first metatarsal head. It causes pain localized to the ball of the foot, directly under the big toe, and worsens with push-off and high-impact activity. Metatarsal pads that offload the sesamoid area are the primary conservative treatment.
The sesamoid bones are unusual: they’re the only bones in the body fully embedded in a tendon, working as a pulley to improve the mechanical advantage of the flexor hallucis brevis muscle. They carry significant compressive loads with each step, which makes them vulnerable to both acute fracture (sesamoid fracture) and chronic overuse inflammation (sesamoiditis).Sesamoiditis, a cause of big toe joint pain, most often affects runners, ballet dancers, and anyone whose activity involves prolonged forefoot loading. The key clinical distinction from other causes of big toe joint pain like gout or hallux rigidus is location: tenderness directly beneath the first metatarsal head (at the ball of the foot), not at the MTP joint itself.
Treatment:
Metatarsal pads: placed just behind (proximal to) the sesamoid bones in the shoe to shift loading away from the inflamed area. The most effective and fastest-acting intervention.Soft-soled footwear: maximum cushioning under the forefoot. Zero-drop or hard-sole shoes are contraindicated during acute sesamoiditis.Activity modification: reduce or cut barefoot walking, hill running, and high-impact activity during recovery.Relative rest: 4 to 8 weeks. Sesamoiditis heals slowly because of the limited blood supply to the sesamoids.Corticosteroid injection: for refractory cases, with caution, since repeated injections can weaken the surrounding tendon.
A sesamoid stress fracture needs imaging (MRI is most sensitive) to tell it apart from sesamoiditis. Fractures may require 6 to 12 weeks in a non-weight-bearing boot, or occasionally surgical excision of a chronically non-healing fragment.
Quick Answer. The right product depends on your condition: toe spacers and bunion splints for bunions (hallux valgus); carbon fiber insoles for hallux rigidus and turf toe; metatarsal gel pads for sesamoiditis; tart cherry extract for gout prevention. Using the wrong product for your condition gives no benefit, and can sometimes make big toe joint pain worse.
1. Correct Toes Toe Spacers
Best for: Bunions (hallux valgus), general forefoot crowding, early-stage bunion prevention
Correct Toes are podiatrist-designed silicone toe spacers that fit between all five toes to progressively restore natural alignment. Unlike generic foam separators, they’re built to be worn inside wide toe-box shoes during activity (walking or running), not just at rest. The goal is passive repositioning of the first metatarsophalangeal angle over months of consistent use. Most effective for Grade 1-2 bunions, with the strongest evidence for symptom relief and slower progression rather than deformity reversal.
Specifications:
Material: Medical-grade silicone
Use: During activity or rest, inside wide toe-box shoes
Sizing: S / M / L / XL
Check Price on Amazon
Best for: Bunions, general toe joint stiffness, post-surgery recovery, hallux valgus maintenance
One of the top-rated toe spreaders on Amazon, with thousands of verified reviews. These gel separators are made for resting use, worn while sitting or lying down, to decompress toe joints and reduce soft-tissue tightening. A more affordable entry point than Correct Toes for people who want symptom relief without the activity-use features. The gel cushions the bony medial eminence and reduces the friction that causes bursitis in bunion patients.
Specifications:
Material: Flexible thermoplastic gel
Use: At rest (30–60 minutes daily)
Size: Universal (one size)
Check Price on Amazon
Best for: Bunion pain management, nighttime alignment maintenance
An adjustable bunion splint with a rigid inner support and a soft outer casing. Worn at night to hold the first toe in a more anatomically correct position while you sleep, reducing the angular stress that speeds bunion progression. It doesn’t reverse deformity in adults (no splint does in skeletally mature bone), but it noticeably reduces morning stiffness and soft-tissue pain in most users. Adjustable velcro straps fit different bunion severities.
Specifications:
Material: Foam lining with rigid thermoplastic support
Use: Nighttime wear
Sizing: S/M and L/XL
Check Price on Amazon
4. Profoot Metatarsal Gel Pads (Insoles)
Best for: Sesamoiditis, hallux rigidus forefoot loading, general metatarsal head pain
Gel pads placed in the shoe just proximal to the metatarsal heads redistribute forefoot loading away from the sesamoid bones and the first MTP joint. Especially effective for sesamoiditis and forefoot pain from hallux rigidus. The gel absorbs impact forces that rigid insoles transfer straight to the inflamed joint. The self-adhesive design keeps them positioned during activity.
Specifications:
Material: Medical-grade gel
Application: Self-adhesive, placed in shoe
Use: Daily wear in any closed-toe shoe
Check Price on Amazon
5. Tart Cherry Extract Capsules
Best for: Gout attack prevention, reducing serum uric acid, joint inflammation
Tart cherries contain anthocyanins and proanthocyanidins shown in clinical trials to lower serum uric acid and reduce gout attack frequency. Two randomized trials, Zhang et al. (2012) and Bell et al. (2014), found that cherry extract cut gout recurrence by about 35% alongside standard care. Unlike colchicine or allopurinol, tart cherry extract is available over the counter and well tolerated.Tart cherry extract is also useful as a general anti-inflammatory supplement, which we discuss in the context of exercise recovery in our creatine for women article.
Specifications:
Dosage used in studies: 480–500 mg tart cherry extract daily (equivalent to ~60 whole cherries)
Form: Capsule or liquid concentrate
Note: Does not replace prescription urate-lowering therapy (allopurinol/febuxostat) for patients with frequent gout
Check Price on Amazon
Best for: Hallux rigidus (Grade 1-3), turf toe recovery, post-cheilectomy maintenance
The single most evidence-supported conservative device for hallux rigidus. Carbon fiber insoles run from the heel to just past the MTP joint (a “Morton’s extension”), creating a rigid platform that prevents big toe dorsiflexion at push-off. This sharply reduces pain with walking by removing the movement that grinds the arthritic joint surfaces. It’s also used in turf toe recovery to protect the healing plantar plate.You have to fit it with a wide toe-box shoe; a narrow or heeled shoe negates the benefit. Some patients need custom-molded orthotics from a podiatrist for best results.
Specifications:
Material: Carbon fiber / fiberglass composite
Extends to: Just distal to the first MTP joint
Shoe requirement: Extra-depth or wide toe-box shoe
Check Price on Amazon
Quick Answer. Fever plus a hot, red, severely swollen joint is a medical emergency. It may be septic arthritis (joint infection), which can destroy a joint within 24 to 48 hours and is life-threatening without IV antibiotics. Don’t assume it’s gout and treat it at home. The two conditions look identical from the outside and can only be told apart by joint aspiration in a clinical setting.
Not all big toe joint pain is benign. These symptoms need urgent or same-day medical evaluation. Don’t wait for a scheduled appointment:
Fever (>38°C / 100.4°F) plus a hot, red, swollen joint: possible septic arthritis; ER evaluation requiredSevere pain with inability to bear weight after an injury: possible fracture or Grade 3 turf toe; X-ray neededRapidly spreading redness, warmth, and streaking up the foot: possible cellulitis or necrotizing fasciitis; ER requiredToe pain plus diabetes: foot complications including Charcot arthropathy and infected ulcers need early podiatry involvement
These warrant a podiatry appointment within 1 to 2 weeks:
Pain lasting beyond 2 weeks despite rest and home care
A mole or lesion that’s growing, changing, or bleeding
A first gout attack (needs uric acid testing and baseline assessment)
Hallux rigidus symptoms that prevent normal walking
The fastest relief depends on the diagnosis. For an acute gout attack: rest, ice (20-minute sessions), elevation, and over-the-counter naproxen sodium (220 mg, two tablets) if you have no kidney disease or peptic ulcer history. For hallux rigidus: a stiff-soled shoe or a carbon fiber insole in your current shoe often gives immediate walking relief. For bunion pain: switching to a wide toe-box shoe and adding a gel toe spacer between the toes reduces irritation within hours. If you're not sure of the diagnosis, hold off on NSAIDs until you see a doctor, since some conditions (like gout on top of CKD) need medication adjustments.
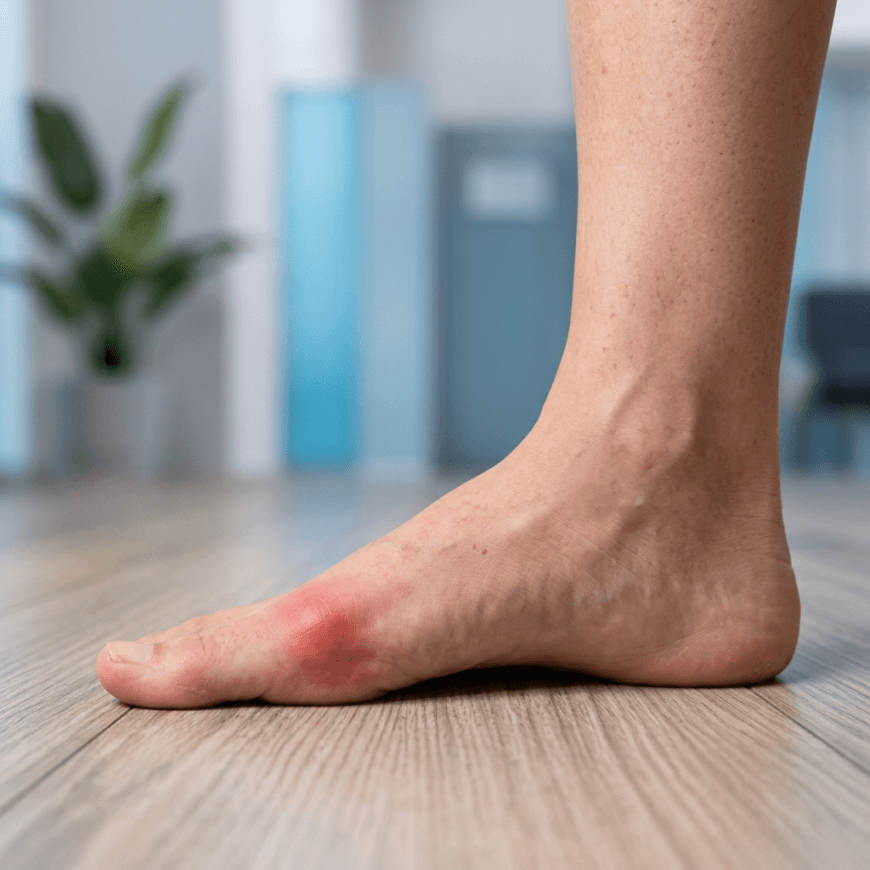
The first MTP joint sits at the body's thermal extremity, and lower local temperature means uric acid reaches its crystallization threshold there before it does in warmer joints. The joint also takes high mechanical stress (forefoot loading and push-off forces), which may help crystals deposit in the cartilage. Over time gout can involve the ankle, knee, wrist, and fingers, but the first MTP joint (podagra) is the classic and most common first presentation.
Footwear likely accelerates hallux rigidus in people with an underlying anatomical predisposition, but it doesn't cause it in an otherwise normal joint. Elevated heels shift body weight forward onto the metatarsal heads, raising MTP stress. Rigid, narrow-toed shoes that restrict natural toe function may contribute to degenerative changes over decades. The underlying risk factors are mostly biomechanical (an elevated metatarsal head, pronation, prior MTP trauma) and genetic. Footwear changes matter for managing symptoms and slowing progression, not for reversal.
No. They're distinct conditions that can coexist. A bunion (hallux valgus) is an angular deformity, where the big toe drifts laterally and the first metatarsal drifts medially, creating a bony bump on the inner foot. Hallux rigidus is an articular degeneration, with cartilage loss and bone spurs that restrict and pain joint motion, especially upward bending. The pain location differs: bunion pain is at the medial eminence (inner side), while hallux rigidus pain is at the dorsal joint and with push-off. Some patients develop both at once, which complicates surgical planning.
For most causes of big toe joint pain, gout, bunions, hallux rigidus Grade 1-3, sesamoiditis, and turf toe, a board-certified podiatrist is the right specialist. Podiatrists complete 4 years of podiatric medical school plus a 3-year residency specifically in foot and ankle conditions and perform the full range of foot surgeries, including bunionectomy, cheilectomy, and arthrodesis. Orthopedic foot-and-ankle surgeons are appropriate for complex reconstructive cases (severe Charcot deformity, severe multi-joint arthritis, complex trauma). Either specialty can perform a first MTP fusion.
Yes, with realistic expectations. The Mediterranean diet lowered CRP (C-reactive protein, a systemic inflammation marker) by about 20% in the PREDIMED trial. Omega-3 fatty acids from fatty fish reduce IL-6 and TNF-alpha, the cytokines that drive inflammatory arthritis flares. Tart cherry anthocyanins cut gout attack frequency, and the related big toe joint pain, by roughly 35% in RCTs. These effects on big toe joint pain are meaningful but modest; they complement medical treatment rather than replace it. The detailed evidence for specific foods is covered in our anti-inflammatory foods guide . For gout specifically, dietary uric acid reduction through purine restriction is only one part of management; most patients with recurrent gout need medication.
This article is for informational purposes only and does not constitute medical advice. Big toe joint pain can have multiple causes requiring different treatments. A sudden, extremely painful, hot, and swollen big toe joint with fever requires urgent medical evaluation to rule out septic arthritis, which is a medical emergency. Please consult a board-certified podiatrist or orthopedic surgeon for diagnosis and personalized treatment recommendations.
Mimo Karam is the founder and writer at LifestyleMine. She writes about daily habits, nutrition, sleep, and emotional wellness, turning research into practical advice for people who want to live healthier without making it complicated.